 LINGCORE SCI
Overlap Weighting in Observational Clinical Research: Defining the Population with Treatment Equipoise
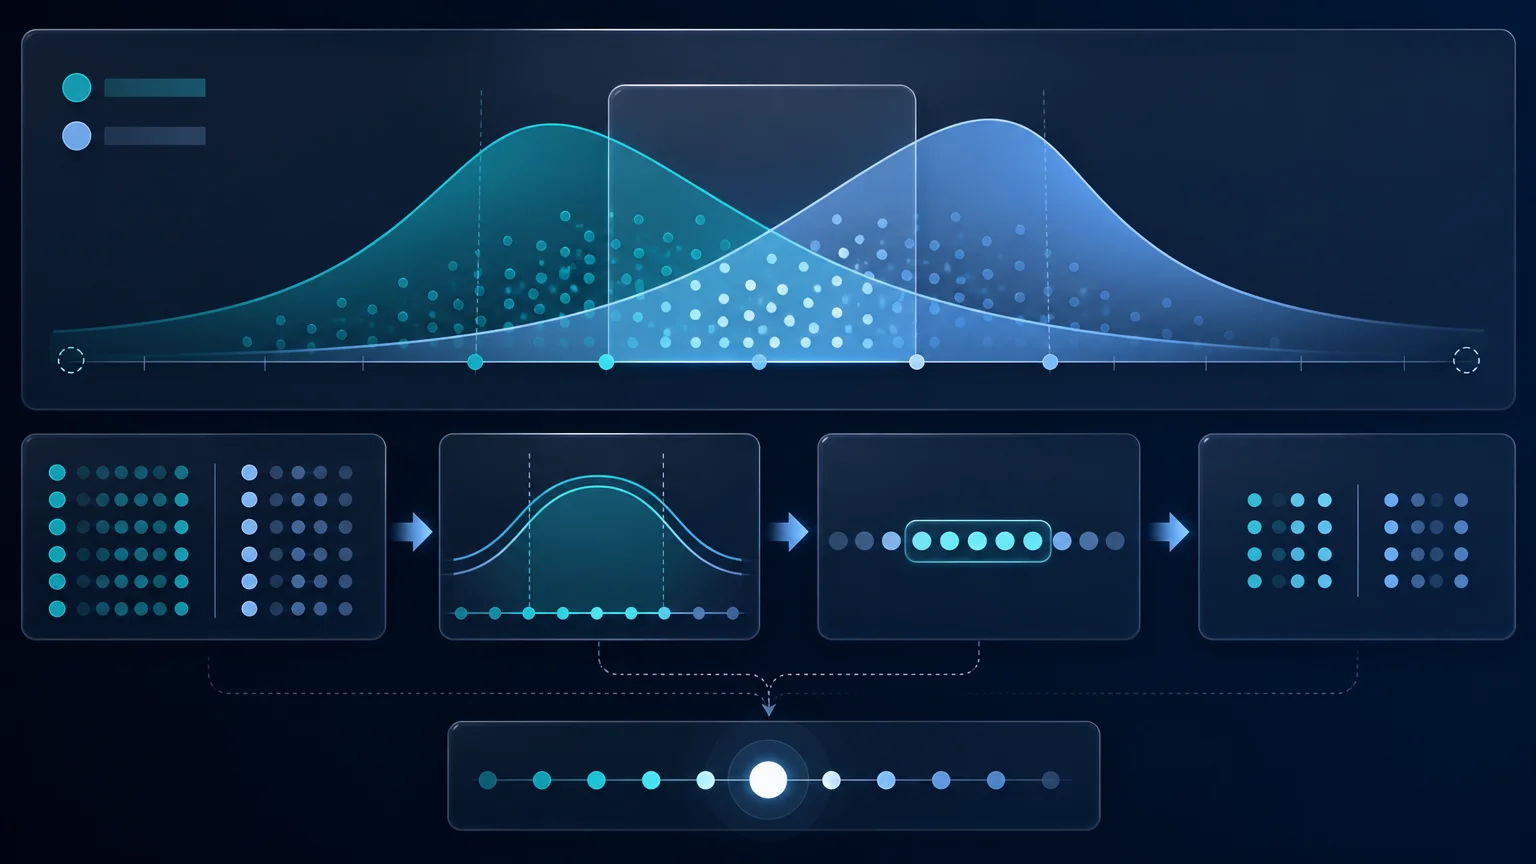
Overlap weighting uses the estimated propensity for the opposite treatment as the weight, emphasizing patients for whom either treatment was clinically plausible. It can reduce the influence of extreme propensity scores and improve covariate balance, but it targets an average treatment effect in the overlap population, not automatically the average treatment effect for everyone in the source cohort.
Observational clinical studies often compare treatments in populations that were not assembled by randomization. Patients receiving one treatment may differ from those receiving another in age, disease severity, comorbidity, prior treatment, access, or clinician preference. A propensity-score analysis can make these differences explicit, but the choice of weighting scheme determines which target population receives the strongest inferential emphasis.
Overlap weighting (OW) is designed for this decision. Instead of giving the largest weights to patients whose observed treatment was unlikely, as ordinary inverse probability of treatment weighting can do, OW gives more weight to patients whose treatment assignment was less predictable from measured covariates. The resulting target population is concentrated where treatment choices overlap. This makes OW especially relevant when investigators face limited overlap, extreme weights, or a clinical question about patients for whom either treatment could reasonably have been selected.
What overlap weighting estimates
Let the propensity score be the probability of receiving treatment conditional on measured pretreatment covariates. For a binary treatment, denote that probability by e(X). The overlap weights are proportional to the probability of receiving the opposite treatment: patients receiving treatment are weighted by 1 − e(X), and patients receiving control are weighted by e(X). The exact estimator and normalization should be stated in the statistical analysis plan.
This rule has a direct clinical interpretation. A treated patient with a propensity score near one was highly expected to receive treatment, so that patient contributes less to the overlap population. A treated patient with a propensity score near one-half had a treatment choice that was less predictable from measured covariates, so that patient contributes more. The same logic applies to control patients. OW therefore shifts attention toward covariate profiles in which both treatment options were observed.
The target is not a technical footnote. An analysis using ordinary IPTW may aim at the average treatment effect in the full source population, whereas OW commonly targets the average treatment effect in the overlap population. These are different causal questions. A manuscript should name the target population and explain why it is clinically relevant before presenting an effect estimate.
Why OW can be more stable than IPTW
Ordinary IPTW assigns a treated patient a weight related to 1/e(X) and a control patient a weight related to 1/[1 − e(X)]. When a propensity score approaches zero or one, the corresponding weight can become very large. A small number of observations may then dominate the estimate, increase variance, reduce effective sample size, and make results sensitive to arbitrary trimming or truncation thresholds.
Overlap weights are bounded for a binary treatment because the opposite-treatment probabilities lie between zero and one. Extreme propensity scores receive smaller weights rather than larger weights. This does not mean that every OW analysis is automatically stable: poor propensity-model calibration, sparse covariate patterns, influential observations, missing covariates, and endpoint-model problems can still undermine inference. The weight distribution and effective sample size should remain part of the diagnostic report.
Li and Li described overlap weights as a way to address extreme propensity scores while emphasizing a target population with covariate overlap. The 2020 JAMA Guide to Statistics and Methods presented OW as a propensity-score method that can mimic important attributes of a randomized clinical trial in an observational setting. These descriptions support the method's rationale, but they do not turn an observational estimate into a randomized estimate.
OW, IPTW, matching, and AIPW: related but different
| Approach | Target or emphasis | Potential strength | Key limitation to report |
|---|---|---|---|
| IPTW | Often the full source population for an ATE, depending on the weights and estimand. | Direct weighting framework with a clear population-level interpretation. | Can produce extreme weights and unstable estimates when overlap is weak. |
| Overlap weighting | Patients with greater treatment equipoise and covariate overlap. | Bounded weights and strong balance properties under the propensity model. | Answers an overlap-population question and may not represent patients outside common support. |
| Propensity-score matching | A matched subset or a matching-specific target population. | Transparent pair or set construction and intuitive balance assessment. | May discard observations and the estimand depends on the matching design. |
| AIPW | An estimand defined by the analyst, using treatment and outcome models. | Doubly robust structure under the relevant assumptions. | Requires careful nuisance-model specification, inference, and diagnostics; it is not the same estimator as OW. |
OW and AIPW are not mutually exclusive concepts. An analyst may use overlap-focused treatment weights within a broader augmented estimator, but the target parameter, correction term, variance method, and software implementation must be specified. Readers should not infer that a paper used AIPW merely because it reported propensity scores and a weighted outcome model.
For readers building a causal-analysis series, the related guides to IPTW, AIPW, TMLE, and the parametric G-formula describe neighboring estimators and their boundaries.
How to diagnose the overlap population
A credible OW analysis begins before weighting. Define time zero, treatment initiation, comparator, follow-up, outcome, and target population. Covariates should be measured before treatment and selected through clinical knowledge and a causal framework. Including variables because they are post-treatment predictors can introduce bias rather than remove it.
Next, inspect the propensity-score model. Plot the score distributions by treatment group, identify sparse regions, review calibration, and assess whether important covariate patterns are represented in both groups. The goal is not to maximize treatment prediction. A highly discriminating model can signal that treatment groups are strongly separated, which may limit the population for which comparative effectiveness is supported.
After applying OW, compare covariate balance before and after weighting. Standardized mean differences are useful descriptive diagnostics, but a threshold is not a proof of no confounding. Report balance for clinically important continuous, binary, and categorical variables, not only the variables that show the largest improvement. Include the distribution of weights, effective sample size, the number of observations contributing to each group, and any missing-data decisions.
If a survival outcome is analyzed, treatment weighting is only one part of the design. Censoring can be informative with respect to measured history, so inverse probability of censoring weighting or another appropriate survival method may be needed. A 2024 American Journal of Epidemiology study examined overlap weighting for restricted mean counterfactual survival times and combined propensity-score weighting with censoring weighting. Its abstract reports advantages of OW over IPTW, trimming, and truncation under moderate and weak overlap in simulations for restricted mean survival time. That is an application-specific methods result, not a guarantee for every clinical dataset.
Five steps for a defensible OW analysis
| Step | Research action | Quality gate |
|---|---|---|
| 1. Define the estimand | State the treatment contrast, time zero, outcome, follow-up, effect scale, and whether the target is the overlap population. | The target population is clinically named before model fitting. |
| 2. Specify pretreatment covariates | Use subject-matter knowledge and a causal diagram to define variables related to confounding and treatment selection. | No post-treatment variable is included as a routine adjustment covariate. |
| 3. Fit and inspect the propensity model | Estimate treatment probabilities and inspect calibration, overlap, sparse regions, and covariate support. | The model is evaluated for causal balance, not only discrimination. |
| 4. Apply OW and assess balance | Report the weight definition, normalization, weighted standardized differences, effective sample size, and influence diagnostics. | Balance and stability are shown for clinically relevant covariates. |
| 5. Estimate and stress-test | Use an outcome and variance method aligned with the endpoint, then compare reasonable propensity specifications and target-population choices. | Conclusions are described as conditional on assumptions and the overlap target. |
Evidence Summary Table
| Source | Contribution | Evidence level and boundary |
|---|---|---|
| Li and Li, American Journal of Epidemiology, 2019 PubMed record | Introduces overlap weights as a strategy for addressing extreme propensity scores and emphasizing patients with greater covariate overlap. | Foundational methods research; assumptions and finite-sample behavior remain study-dependent. |
| Thomas, Li, and Pencina, JAMA, 2020 PubMed record | Clinical methods guide explaining how OW can mimic selected attributes of a randomized clinical trial in observational research. | Methods guidance; it does not eliminate confounding or establish exchangeability. |
| Cao et al., American Journal of Epidemiology, 2024 Open-access article | Studies OW for restricted mean counterfactual survival times and addresses treatment and censoring weights. | Survival-methods application with simulation evidence; endpoint-specific implementation is required. |
| Propensity scores used as overlap weights, 2024 PubMed record | Examines the exact covariate-balance properties of propensity scores used as overlap weights. | Methodological evidence; exact balance depends on the propensity-score model and covariate representation. |
| When and why to use overlap weighting, 2025 Journal of Clinical Epidemiology article | Clarifies when OW is appropriate and emphasizes that it answers a different target-population question from other propensity-score methods. | Recent practice-oriented guidance; investigators must still justify the target population for their study. |
What reviewers should be able to see
A reviewer should be able to reconstruct the weighting analysis from the Methods section. The manuscript should define the treatment assignment rule, list the covariates and their timing, state the propensity-score model, show the weight formula, identify the target estimand, and describe the outcome and censoring analysis. It should also show pre- and post-weighting balance, score overlap, weight summaries, effective sample size, and the handling of missing data.
Interpretation should match the target population. A favorable effect among patients with treatment equipoise should not be generalized to patients whose clinical profiles strongly predicted one treatment unless transportability is separately justified. Likewise, an improvement in measured balance is not evidence that all sources of confounding have been controlled. The strongest report makes these limits visible instead of presenting OW as a universal replacement for design-based reasoning.
Researcher's Toolkit
Use Lingcore SCI to organize and audit an overlap-weighting manuscript:
- Paper Analyzer: extract the estimand, treatment definition, covariate timing, propensity model, balance diagnostics, and target-population language from a paper.
- Review Builder: compare OW with IPTW, matching, AIPW, TMLE, and other causal estimators using source-linked evidence.
- Journal Matcher: identify journals aligned with causal inference, pharmacoepidemiology, real-world evidence, and clinical outcomes research.