 LINGCORE SCI
The Parametric G-Formula in Clinical Causal Inference: Addressing Time-Varying Confounding under Treatment-Confounder Feedback
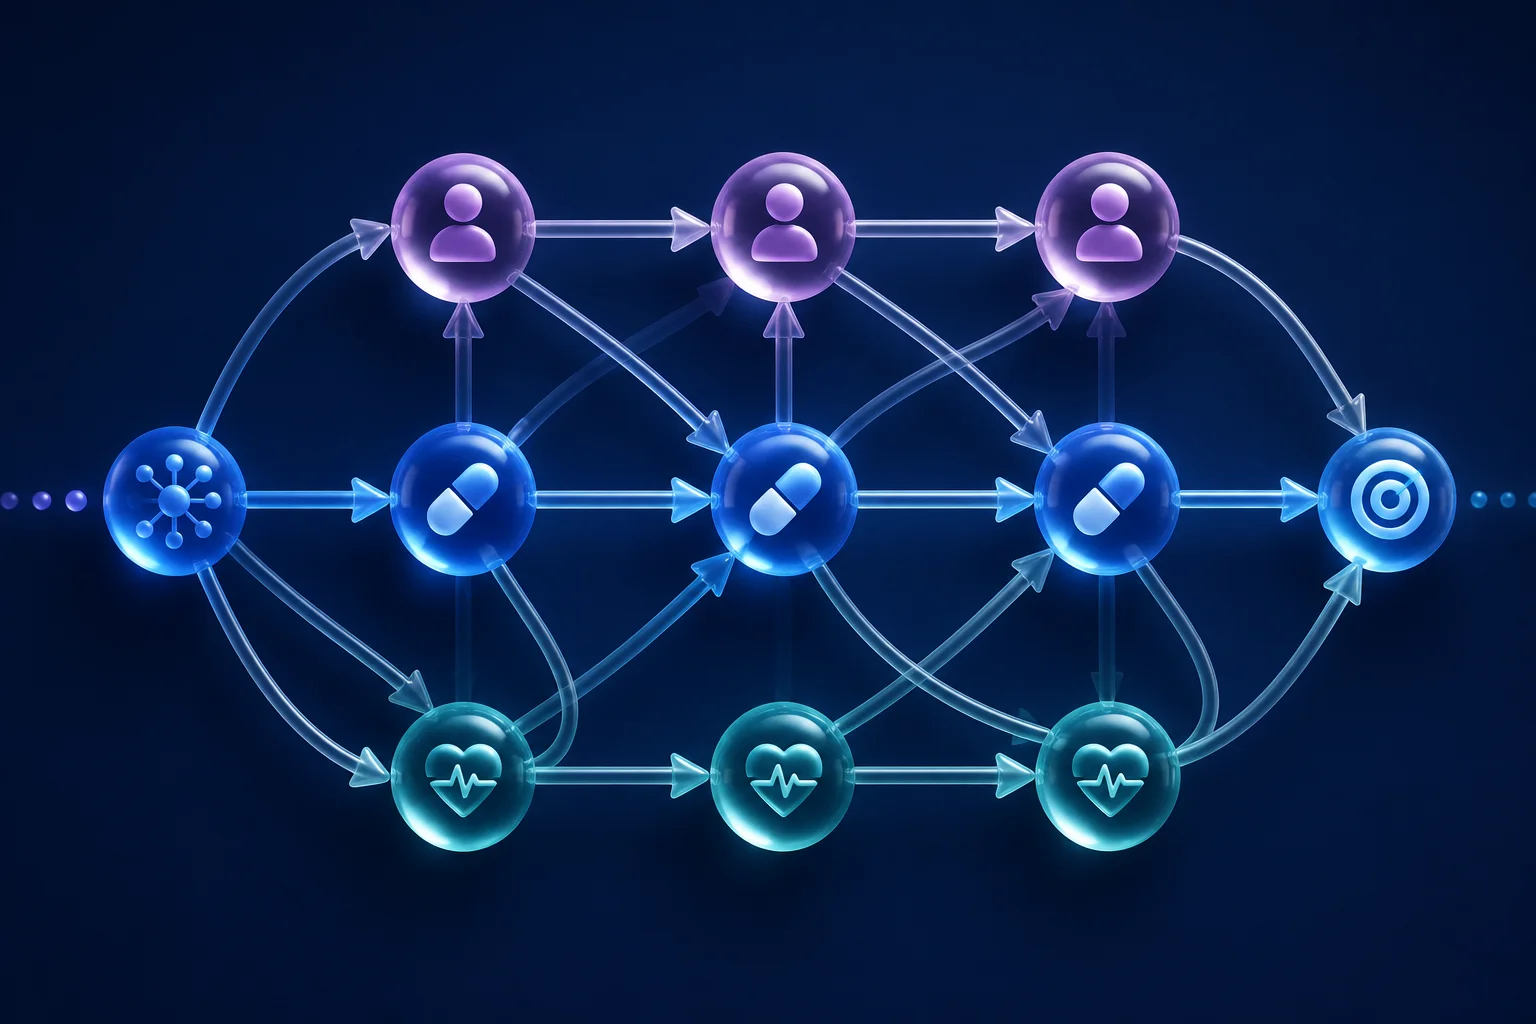
The parametric G-formula (G-computation) is a generalization of standardization that estimates treatment effects under time-varying confounding with treatment-confounder feedback. By sequentially simulating counterfactual outcomes under hypothetical treatment policies, it avoids the bias that plagues standard regression models when confounders act as both mediators of past treatment and predictors of future treatment.
In observational clinical studies with longitudinal follow-up, analyzing the effect of sustained treatments is notoriously difficult. Patients do not receive a single treatment at baseline and remain on it statically. Instead, clinical decisions are dynamic, evolving at each visit based on the patient's changing health status. This gives rise to a complex phenomenon known as treatment-confounder feedback.
Consider a cohort of HIV-positive patients. The decision to initiate or adjust antiretroviral therapy (ART) depends heavily on the patient's CD4 cell count—a time-varying confounder. However, CD4 count is also affected by past ART exposure. CD4 count is simultaneously a confounder (predicts future treatment), a mediator (on the causal pathway from past treatment to the final outcome, such as mortality), and an outcome of past treatment. When time-varying confounders are affected by prior treatment, standard statistical approaches fail catastrophically. The parametric G-formula, first formulated by James Robins in 1986, is the foundational causal inference tool designed to resolve this challenge.
The Double-Bind of Standard Regression
To understand why we need the G-formula, we must examine why standard methods break down in the presence of treatment-confounder feedback. If we run a standard regression model (such as Cox proportional hazards or logistic regression) and control for the time-varying confounder (CD4 count) by simply adding it as a covariate, we introduce two distinct types of bias:
- Overadjustment Bias: Because the time-varying confounder is a mediator of the treatment's past effect, adjusting for it blocks the causal path from past treatment to the outcome, leading to an underestimation of the treatment's true cumulative effect.
- Collider-Stratification Bias: If there is an unmeasured confounder of the mediator-outcome relationship, adjusting for the mediator (which acts as a collider) opens a back-door path between past treatment and the outcome, introducing spurious associations.
Conversely, if we choose not to adjust for the time-varying confounder, we suffer from classic confounding bias because CD4 count strongly predicts future treatment decisions. Standard regression is therefore caught in a statistical double-bind: adjusting causes bias, and not adjusting also causes bias. The G-formula resolves this by mathematically simulating the entire clinical course under hypothetical, well-defined treatment strategies.
The Principle of G-Computation: Sequential Standardization
At its core, the G-formula is a generalization of classical direct standardization to settings with time-varying treatments and confounders. It operates by breaking down the joint distribution of the treatment, confounders, and outcome into a series of conditional probabilities. These conditional distributions are sequentially multiplied and integrated (or summed) over the distribution of the confounders.
Mathematically, the G-formula simulates what the outcome distribution would look like if we forced everyone in the population to follow a specific, counterfactual treatment plan—such as "always treat" or "never treat." Instead of adjusting for confounders in a regression model to estimate an association, the G-formula models the predictors of the confounders themselves, simulating their progression over time under the designated treatment rule.
Under three standard causal assumptions—exchangeability (no unmeasured confounding), positivity (non-zero probability of receiving any treatment option), and consistency (well-defined treatment versions)—the G-formula successfully estimates the true counterfactual distribution, bypassing both overadjustment and collider-stratification biases.
Comparing Causal Inference Methods for Time-Varying Confounding
Choosing between G-estimation, IPTW (via Marginal Structural Models), TMLE, and the Parametric G-formula depends heavily on sample size, model misspecification risk, and the complexity of the treatment regime.
| Method | Core Mechanism | Strengths | Weaknesses / Limitations |
|---|---|---|---|
| Parametric G-Formula | Simulates counterfactuals by modeling outcomes and confounders sequentially. | Highly efficient; easily handles complex, joint, or dynamic treatment regimes. | Vulnerable to model misspecification across all sequential equations (g-null paradox). |
| IPTW (MSMs) | Weights the population to create a pseudo-population where treatment is unconfounded. | Relatively simple to implement; robust to outcome model misspecification. | Unstable in the presence of extreme weights (near-violations of positivity). |
| TMLE | Double-robust estimation combining outcome modeling and propensity scores with machine learning. | Double-robust; asymptotically efficient; integrates machine learning seamlessly. | Computationally demanding; highly complex to program for time-varying settings. |
A Step-by-Step Path to Implementing the Parametric G-Formula
Because analytical integration of multiple time-varying confounders and treatments is practically impossible, the G-formula is implemented computationally using **parametric g-computation** via Monte Carlo simulation. The process follows a structured, multi-step pipeline.
| Step | Technical Action | Quality Gate / Safety Check | |
|---|---|---|---|
| 1. Model Fitting | Fit parametric regression models for each time-varying confounder, the treatment, and the final outcome at each time point, using prior history as predictors. | Ensure models are rich enough to capture non-linearities and interactions. Check for residual confounding. | Model misspecification in early steps propagates and biases all subsequent simulations. |
| 2. Monte Carlo Simulation | Simulate a large cohort of virtual subjects starting from the observed baseline covariates. For each subject, simulate confounder values sequentially. | Ensure the simulated sample size (e.g., 10,000+ virtual subjects) is large enough to minimize simulation error. | Large variance in simulated confounders can indicate model instability. Check distribution fits. |
| 3. Intervene with Policy | At each time step, instead of simulating treatment from the propensity model, force treatment to follow the hypothetical protocol (e.g., "Always Treat"). | Confirm the intervention is medically realistic and mathematically well-defined. Specify exact rules. | Violations of positivity (e.g., intervening on a policy where no one actually qualifies) yield unstable estimates. |
| 4. Outcome Simulation & Pooling | Simulate the final outcome for each virtual subject under the intervened paths. Pool the results to calculate the mean counterfactual outcome. | Verify that the simulated outcome distributions align with the clinical plausibility boundaries of the disease. | Unrealistic outcomes (e.g., survival probabilities rising over time) indicate simulation error. |
| 5. Bootstrap Variance | Repeat the entire process (steps 1–4) on 200–500 bootstrap samples of the original observational dataset to calculate confidence intervals. | Check that the bootstrap distribution is symmetric. Ensure sufficient computing power is allocated. | Standard analytical standard errors are invalid due to the multi-stage simulation; bootstrapping is mandatory. |
Addressing the G-Null Paradox
A critical technical caveat of the parametric G-formula is the **G-null paradox**. This paradox occurs when the parametric models used for the confounders and treatments are internally inconsistent with the null hypothesis of no treatment effect. If the null hypothesis is true, but we fit separate parametric models for each mediator and confounder at every time point, the G-formula may mathematically force a non-zero treatment effect simply due to minor parametric misspecifications.
To mitigate this risk, investigators should conduct rigorous sensitivity analyses, compare G-formula estimates with semi-parametric methods (like IPTW or G-estimation) that are less prone to this specific paradox, and utilize flexible modeling techniques (such as splines or machine learning algorithms within the G-computation framework) to reduce parametric misspecification. In contemporary causal inference, semi-parametric G-computation and double-robust methods have become preferred when model misspecification is a primary concern.
Reporting Guidelines and Peer-Review Checklist
When presenting a study utilizing the parametric G-formula in high-impact SCI journals, authors must ensure complete methodological transparency. Editors and reviewers actively look for the following disclosures:
- DAG Presentation: Provide a clear Directed Acyclic Graph (DAG) visualizing the hypothesized relationships, time-varying confounders, and treatment-confounder feedback loops.
- Model Specifications: Detail every parametric regression model used in the simulation pipeline (distributions, link functions, covariates, and lag-times).
- Positivity Assessment: Explicitly discuss the positivity assumption. Document whether there are specific clinical profiles where certain treatment decisions are completely deterministic (which violates positivity).
- Bootstrap Parameters: State the exact number of bootstrap repetitions used to calculate the 95% confidence intervals.
Researcher's Toolkit: Optimize Causal Inference Reporting
Leverage Lingcore Health's specialized SCI tools to ensure your causal analysis meets the highest reporting and peer-review standards:
- Paper Analyzer: Run an automated pre-submission compliance audit on your manuscript to check for proper confounding adjustments, causal assumptions, and reporting standards.
- Review Builder: Generate citation-linked methodological reviews, comparing G-formula, IPTW, and TMLE approaches tailored to your specific clinical area.
- Journal Matcher: Find high-impact SCI journals with editors and reviewers who specialize in advanced causal inference and epidemiologic methodology.
These tools are designed to streamline evidence synthesis and manuscript preparation. Clinicians and biostatisticians remain fully responsible for verifying study assumptions, checking model diagnostics, and ensuring clinical and ethical validity.
Conclusion
The parametric G-formula represents a pinnacle of clinical epidemiology, providing a mathematically elegant and highly efficient solution to the otherwise intractable problem of treatment-confounder feedback. By transitioning from restrictive standard regression models to sequential counterfactual simulation, researchers can leverage longitudinal observational cohorts to answer complex, real-world clinical questions that randomized controlled trials cannot address. When combined with rigorous diagnostic checks and reported with absolute transparency, G-formula analyses provide exceptionally robust evidence that easily withstands peer-review scrutiny in top-tier medical journals.
Medical Disclaimer
This article is for educational and medical research purposes only. It does not constitute medical advice, clinical diagnosis, or treatment recommendations. All statistical methods, causal assumptions, and study designs must be verified by qualified biostatisticians and clinical investigators in accordance with institutional, ethical, and regulatory guidelines before implementation.