 LINGCORE SCI
Win Ratio in Clinical Trials: Designing Hierarchical Composite Endpoints Without Hiding Component Effects
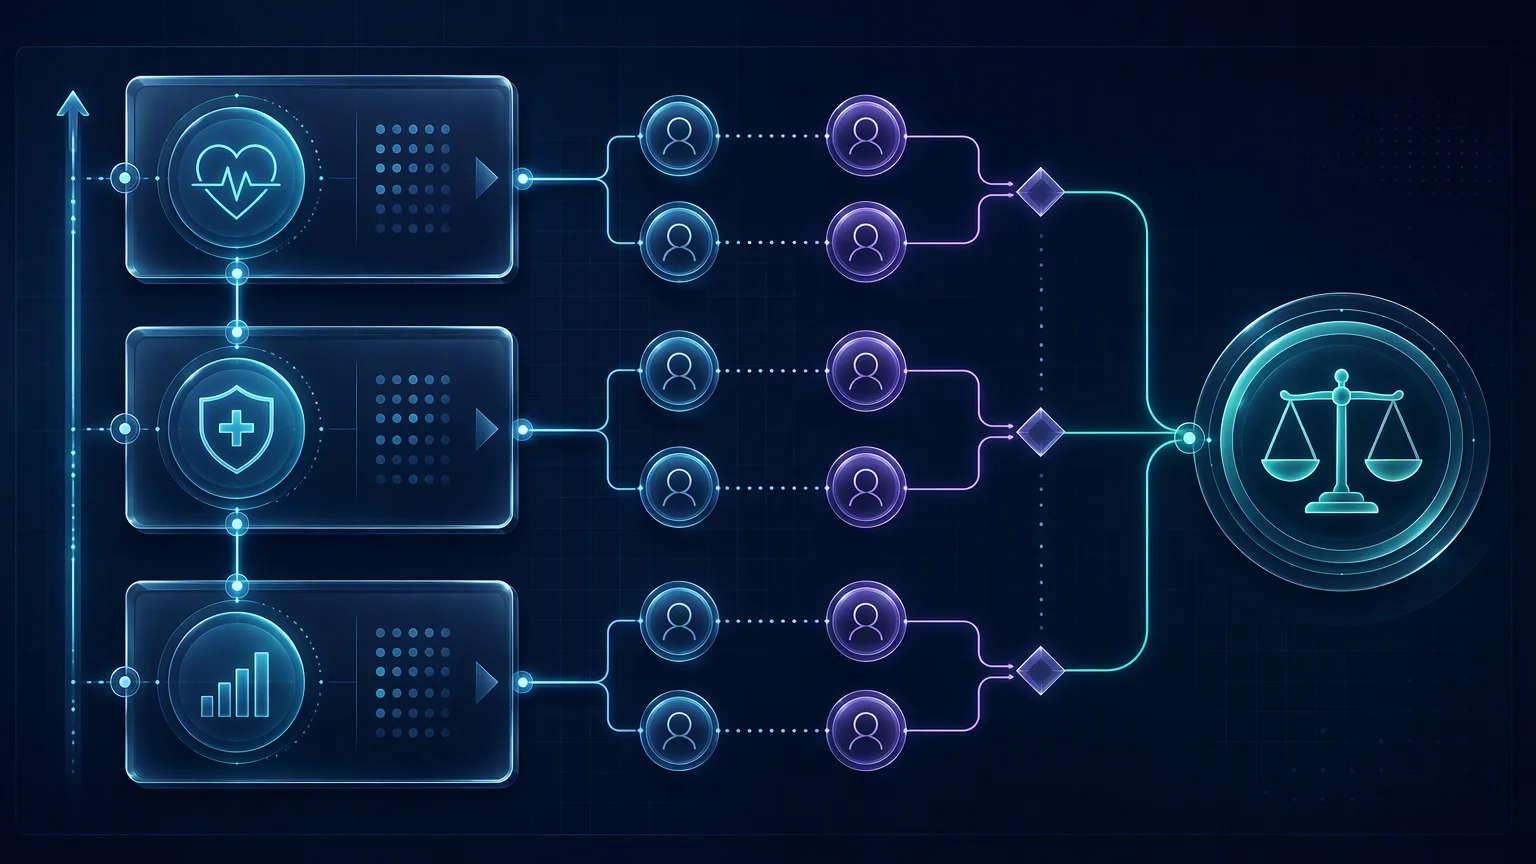
The win ratio compares treated and control participants pair by pair using a prespecified clinical hierarchy, giving priority to more important outcomes before considering lower-priority events or quantitative measures. It can use more component information than a time-to-first-event composite, but it is a relative, hierarchy-dependent summary and should be reported with component results, absolute measures, and the win difference.
Composite endpoints are common in clinical trials because a single outcome may be too infrequent or too slow to support a practical decision. A cardiovascular trial might combine death, hospitalization, and a patient-reported or functional measure. The attraction is clear: the trial can use more outcome information than a single component alone. The difficulty is that a conventional time-to-first-event analysis gives the first event priority, even when the first event is not the most clinically important outcome.
The win ratio offers a different structure. It compares participants across treatment groups in pairs and resolves each pair through a prespecified hierarchy. A pair may first be compared on death, then on a serious non-fatal event, then on hospitalization, and finally on a quantitative measure if the higher-priority outcomes do not distinguish the pair. The result is a relative summary of how often the treatment participant wins over the control participant according to the clinical priorities defined before analysis.
This method can be useful when the research question is explicitly hierarchical and when investigators want fatal or irreversible outcomes to dominate less consequential events. It is not automatically superior to a conventional composite. The hierarchy is a scientific choice, the win ratio is not an individual treatment probability, and the final result can be driven by lower-priority components unless the component contributions are shown.
What the win ratio measures
Let one participant come from the intervention group and one from the control group. The analysis compares the pair on the highest-priority component. If one participant has a better outcome on that component, the pair produces a win for that participant and the comparison stops. If the comparison is tied or uninformative, the analysis moves to the next component in the hierarchy. The process continues until the pair is resolved or remains tied across all specified levels.
The win ratio is commonly expressed as the number of treatment wins divided by the number of control wins, after the prespecified pairwise rules are applied. Related summaries include the win difference, often understood as the proportion in favor of treatment minus the proportion in favor of control, and the proportion in favor of treatment. These measures answer related but not identical questions and should not be treated as interchangeable without explanation.
The hierarchy can combine different outcome types. Death and time-to-event outcomes may be placed above hospitalization, while a quantitative functional or quality-of-life measure may be included lower in the order. The method therefore provides a framework for respecting clinical priorities that are difficult to encode in a simple first-event composite.
Why hierarchy is a protocol decision
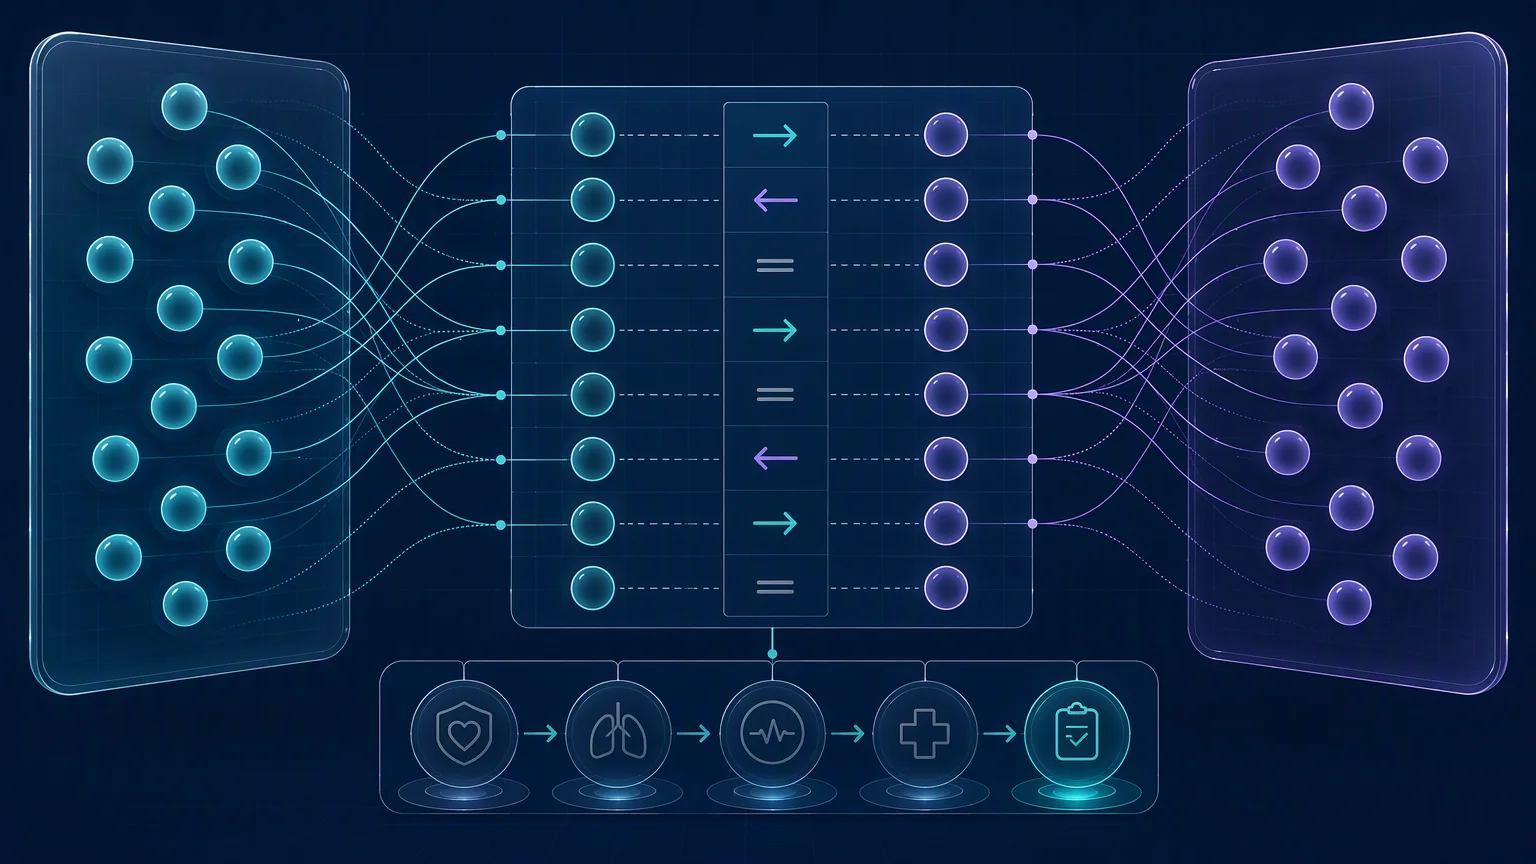
The ordering of components is not a technical detail to be chosen after the data are inspected. It represents the investigators’ view of which outcomes matter most for the clinical decision. A hierarchy that places death first and hospitalization second makes a different scientific statement from one that gives equal weight to all first events. The order should be justified by clinical importance, patient priorities, regulatory context, and the intended decision.
Each component also needs a clear comparison rule. For a time-to-event component, the analysis may compare earlier versus later event occurrence, while for a quantitative outcome it may compare the value at a defined time point or change from baseline. Ties, administrative censoring, missing quantitative measures, recurrent events, and competing risks need prespecified handling. If rules change after reviewing treatment-group patterns, the resulting win ratio is vulnerable to selective interpretation.
A clinically meaningful hierarchy should be understandable to trial participants, clinicians, and reviewers. Avoid an order that appears to be chosen solely to maximize statistical power. The fact that a component is frequent does not make it more important, and a lower-priority component should not be used to dilute a null or unfavorable result on the most serious outcome.
Win ratio versus a time-to-first-event composite
A conventional time-to-first-event analysis records the first qualifying event for each participant. This is simple, but later events are ignored after the first event, and a relatively frequent lower-severity event can dominate the composite. The win ratio can preserve more information by comparing pairs through a priority order and, in some designs, incorporating later or quantitative outcomes.
The methods answer different estimands. A hazard ratio from a time-to-first-event analysis compares event rates under a proportional-hazards model or another time-to-event model. A win ratio summarizes pairwise wins under a hierarchy. One is not a direct replacement for the other, and a difference in statistical significance does not by itself indicate which method is clinically preferable.
| Feature | Time-to-first-event composite | Win-ratio hierarchy |
|---|---|---|
| Primary structure | Time until the first qualifying event. | Pairwise comparison through a prespecified outcome hierarchy. |
| Clinical priority | All included first events may be treated similarly unless separately modeled. | Higher-priority outcomes are compared before lower-priority outcomes. |
| Information use | Events after the first qualifying event are generally not part of the primary comparison. | Can incorporate multiple component types and additional information under defined rules. |
| Main interpretation | Relative time-to-event contrast, often a hazard ratio. | Relative pairwise win contrast, often accompanied by win difference. |
| Key risk | Frequent lower-severity components can drive the composite. | The hierarchy and component drivers can be hidden if reporting is incomplete. |
Interpreting the win ratio without overclaiming
A win ratio above one means that, under the specified pairing and hierarchy, treatment wins were more frequent than control wins. It does not mean that every patient benefits, that the probability of individual benefit is the same as the win ratio, or that the treatment reduces absolute risk by a directly readable percentage. The population-level pairwise summary should be kept distinct from an individual prognosis.
The win ratio is also not automatically equivalent to a number needed to treat. Critical reviews have emphasized that relative pairwise summaries may be difficult to translate into absolute risk, absolute event reduction, or NNT/NNH. Readers need the component-specific event counts or survival summaries, the win difference or proportion in favor, and an explanation of which outcomes contributed most to the overall result.
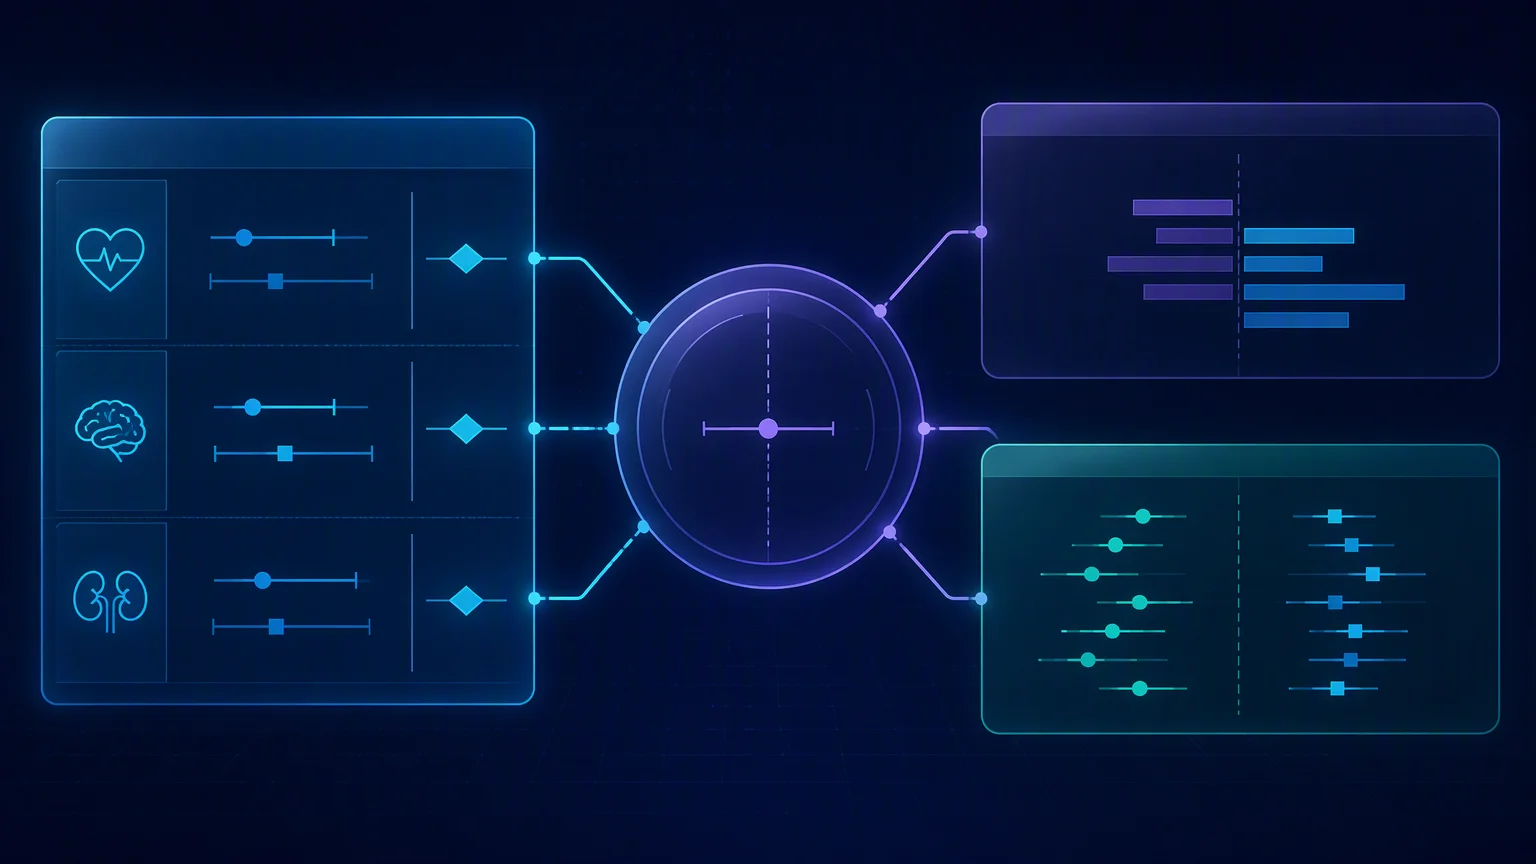
Component-level reporting is especially important when the highest-priority component is uncommon. A trial may have a favorable overall win ratio because many pairs are resolved by a frequent lower-priority hospitalization or functional measure, while the most serious outcome shows little difference. That is not necessarily a flaw in the method, but it changes the clinical interpretation and must be visible.
Design and sample-size considerations
Sample-size planning for a win-ratio endpoint depends on the anticipated pairwise win probability, the distribution of events across hierarchy levels, censoring, ties, allocation ratio, and the proportion of pairs that can be resolved. A conventional event-count formula for a time-to-first-event hazard ratio may not transfer directly because the information structure is pairwise and hierarchical.
Investigators should simulate plausible scenarios before finalizing the design. Scenarios should include no treatment effect, a benefit concentrated in the highest-priority component, a benefit only in lower-priority components, competing effects across components, different censoring patterns, missing quantitative outcomes, and different event rates. The design should be evaluated for power, bias, confidence-interval coverage, and the probability that the hierarchy is actually informative.
The sample-size plan should state the primary win-ratio definition, the pairwise comparison rules, the expected win difference or win probability, the treatment allocation, the follow-up horizon, and how incomplete pairs are handled. If the analysis includes recurrent or quantitative outcomes, the simulation should represent their timing and measurement process rather than treating them as independent labels.
Evidence from cardiovascular and heart-failure trials
Win-ratio methods have been used most extensively in cardiovascular randomized trials, including heart-failure studies. A practical review described how a hierarchy can combine death with non-fatal cardiovascular hospitalization and quantitative outcomes while using more of the available component information than a simple first-event analysis.
A later review of cardiovascular randomized trials found heterogeneous uses of hierarchical composites. Many studies combined event outcomes and quantitative measures, while others used the hierarchy to represent clinical priorities among event outcomes. The review recommended clearer communication of which components drove the result, complementary win-difference reporting, and prespecification of the outcomes and analysis.
These applications illustrate both the potential and the boundary. A hierarchy can make a composite endpoint more aligned with clinical priorities, but it also increases the responsibility to explain the order, the component definitions, the number of unresolved pairs, and the contribution of each component. A single favorable summary number is not enough for a clinically interpretable report.
Actionable Steps: Plan and report a win-ratio analysis
| Step | Research action | Quality gate |
|---|---|---|
| 1. Define the clinical priority | Write the composite hierarchy in plain language and justify why each outcome precedes the next. | The order is clinically defensible and locked before unblinding or outcome-driven revision. |
| 2. Specify pairwise rules | Define treatment/control pairing, time-to-event comparisons, quantitative outcome windows, ties, censoring, missing measures, and competing events. | Every possible pair and every hierarchy level has a reproducible decision rule. |
| 3. Simulate the design | Estimate expected win probability, win difference, component rates, power, coverage, censoring sensitivity, and the effect of alternative component patterns. | Sample size and follow-up are linked to the actual hierarchical information structure. |
| 4. Analyze the full hierarchy | Report win ratio, win difference or proportion in favor, confidence intervals, unresolved pairs, and component-level contributions. | The overall result can be traced to the outcomes that generated the wins and losses. |
| 5. Translate clinically | Add absolute risks, event-specific estimates, survival summaries, or quantitative effects and explain what the relative pairwise result does and does not mean. | Readers can assess clinical importance without converting the win ratio into an unsupported NNT or individual probability. |
Common reporting failures
The first failure is choosing the hierarchy after observing event frequencies or treatment-group patterns. This turns a clinical-priority method into a data-driven ranking and can make the result vulnerable to selective reporting.
The second failure is reporting the win ratio without the win difference, component-specific effects, or absolute measures. The ratio may be statistically significant but clinically difficult to interpret if the underlying event counts and component drivers are hidden.
The third failure is describing a win ratio above one as the probability that a randomly selected patient benefits. The win ratio is a population-level pairwise summary. It does not provide an individual treatment response probability or guarantee a uniform effect.
The fourth failure is treating every composite component as equally meaningful after using a hierarchy. If death is the highest-priority outcome, the manuscript should report how many comparisons were resolved at death and whether the overall conclusion depends mainly on later components.
The fifth failure is using conventional sample-size assumptions without simulating the hierarchical endpoint. The number of events, proportion of ties, component ordering, censoring, and quantitative outcomes can materially change power and precision.
The sixth failure is presenting the win ratio as a replacement for all conventional analyses. A prespecified complementary analysis of components, absolute risks, time-to-event outcomes, or patient-reported measures can make the result more transparent and can identify clinically relevant disagreement between summary measures.
Evidence Summary Table
| Evidence or methods source | What it supports | Level and boundary |
|---|---|---|
| Pocock et al., 2012 Foundational method | Introduces pairwise hierarchical comparison for composite endpoints based on clinical priorities. | Foundational methodology; hierarchy and comparison rules must be prespecified. |
| Pocock et al., 2020 Practical trial guidance | Explains combining death, non-fatal outcomes, and quantitative measures and discusses trial design and reporting. | Methods guidance; design assumptions and sample-size planning remain study-specific. |
| Pocock et al., 2024 Cardiology review | Summarizes lessons, developments, and wise future use of win ratio in cardiology trials. | Review; recommendations should be adapted to the trial estimand and endpoints. |
| Pocock et al., 2025/2026 Scoping review and guidance | Reviews 36 cardiovascular RCTs and recommends win difference, component drivers, and clear prespecification. | Scoping review; use patterns are heterogeneous and not a universal template. |
| Packer et al., 2023 Critical methods paper | Describes fallacies in interpretation, including difficulty deriving absolute risk or NNT from win ratio alone. | Critical appraisal; complements but does not replace primary analysis guidance. |
| Yu & Ganju, 2022 Sample-size methods | Provides sample-size methodology for a win-ratio endpoint. | Formula-based methods; inputs must reflect the planned hierarchy and event structure. |
Researcher's Toolkit: Audit a Hierarchical Composite
Use Lingcore SCI tools to organize and quality-check win-ratio research:
- Paper Analyzer: Extract hierarchy order, component definitions, pairwise rules, censoring, ties, sample-size assumptions, and component-level results.
- Review Builder: Build a citation-linked comparison of win ratio, win difference, conventional composites, and component-specific analyses.
- Journal Matcher: Compare journals publishing cardiovascular trials, composite endpoints, clinical statistics, and trial methodology.
These tools support evidence organization and reporting quality. Researchers remain responsible for the estimand, hierarchy, statistical analysis plan, clinical interpretation, and regulatory or institutional review.
Conclusion
The win ratio is useful when a clinical trial has multiple outcomes with an explicit order of importance and when a conventional first-event composite does not adequately express that priority. Its pairwise structure can use information from different component types and provide a clinically meaningful relative summary.
Its credibility depends on transparency. Investigators should prespecify the hierarchy and pairwise rules, simulate sample size and operating characteristics, report win difference and component drivers, and add absolute measures that help clinicians interpret magnitude. Used with those safeguards, the win ratio can make a composite endpoint more clinically intentional without hiding which outcomes actually determine the conclusion.
Medical Disclaimer
This article is for medical research and educational purposes only. It does not provide medical advice, diagnosis, treatment recommendations, or a substitute for clinical, statistical, regulatory, or institutional review. Researchers must verify the cited sources, assumptions, endpoint definitions, analysis plan, and validation results before using win-ratio methods in a study or decision.