 LINGCORE SCI
Handling Non-Proportional Hazards in Survival Analysis: Practical Solutions for Time-Varying Effects in Clinical Research
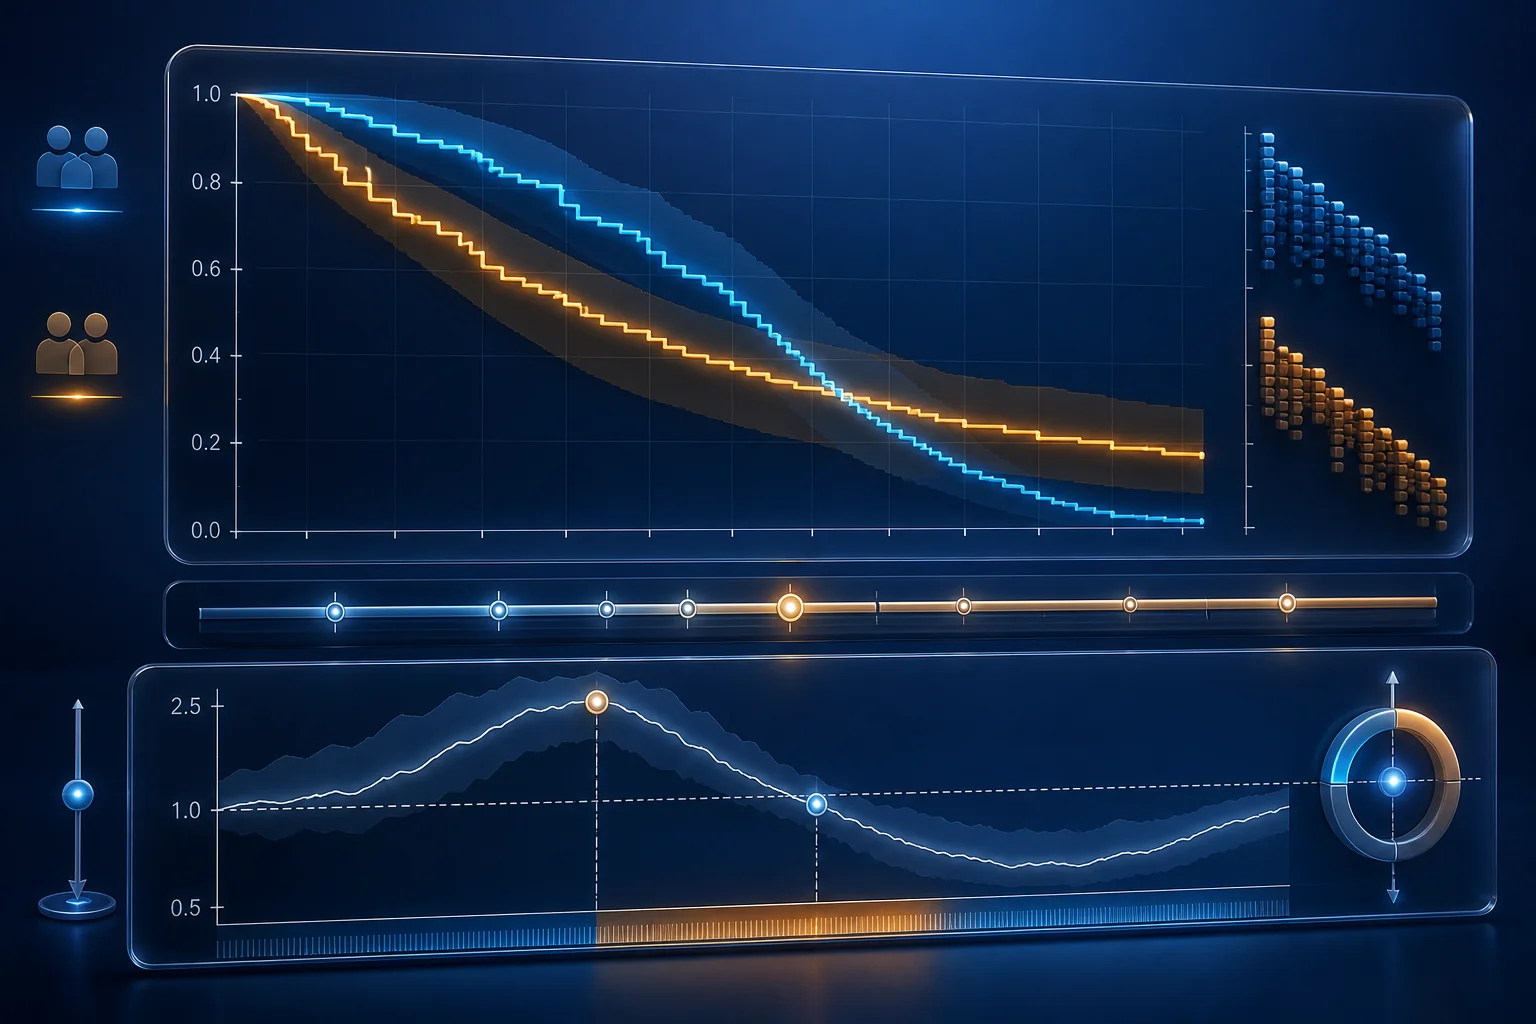
Non-proportional hazards (NPH) occur when the ratio of hazards between treatment groups changes over time. To prevent bias, clinical researchers must test the proportional hazards assumption using Schoenfeld residuals; when violated, they must apply extended Cox models with time-varying coefficients, stratified Cox regression, or restricted mean survival time (RMST).
The Cox proportional hazards (PH) model is the undisputed workhorse of clinical survival analysis. Its core appeal lies in its simplicity: a single hazard ratio (HR) summarizes the relative treatment effect over the entire follow-up period. However, this simplicity rests on a strict and fragile assumption: the hazard ratio must remain constant over time. When the hazard ratio varies—a phenomenon known as non-proportional hazards (NPH)—reporting a single "average" hazard ratio is clinically misleading and statistically invalid.
In modern oncology trials, particularly those involving cancer immunotherapy, violations of the proportional hazards assumption are increasingly common. Immunotherapies often exhibit a delayed treatment effect; early survival curves may overlap or even cross, followed by a dramatic divergence months later. Forcing a standard Cox model onto such data violates the PH assumption, dramatically underestimating the late-stage survival benefit, underpowering the study, and masking the true time-dependent nature of the therapeutic effect. Recognizing, testing, and resolving non-proportional hazards is a regulatory requirement and a hallmark of rigorous clinical methodology.
What Causes Non-Proportional Hazards?
Non-proportional hazards are driven by clinical and biological mechanisms. Understanding the underlying cause is crucial, as the nature of the violation determines the correct statistical remedy. The three most common clinical drivers are:
- Delayed Treatment Effects: Common in immunotherapy. The therapeutic mechanism requires weeks or months to stimulate the immune system, resulting in identical hazards between treatment and control arms initially, followed by a significant survival benefit later (the hazard ratio decreases over time).
- Waning Treatment Effects: Often seen in surgical interventions or short-course pharmacotherapies. A treatment may provide a massive survival benefit early on, but over time, the effect fades due to treatment cessation, disease recurrence, or physiological adaptation (the hazard ratio moves toward 1.0 over time).
- Selection Bias (Exhaustion of Susceptibles): In heterogeneous cohorts, high-risk individuals in the control group die early, leaving behind a highly selected group of healthier, low-risk survivors. Consequently, the mortality rate in the control group naturally declines, causing the curves to converge and making the treatment appear less effective over time.
Testing the Proportional Hazards Assumption
Investigators must never assume proportional hazards are satisfied. Peer reviewers and regulatory bodies expect formal diagnostics to be documented in the manuscript. The standard testing workflow includes:
1. Graphical Inspection: Kaplan-Meier and Log-Log Plots
While Kaplan-Meier curves are invaluable, looking at them is insufficient. Crossing, converging, or diverging curves are strong visual indicators of non-proportionality. A more formal visual check is the log-log survival plot: a plot of -ln(-ln(S(t))) against ln(t). Under proportional hazards, the curves for different treatment arms should be approximately parallel. Parallelism indicates the assumption holds; convergence or crossing indicates a violation.
2. Schoenfeld Residual Tests (The Gold Standard)
The Schoenfeld residual test is the most rigorous and widely accepted diagnostic. Schoenfeld residuals represent the difference between the observed covariate value for an individual who failed at a given time and the expected value under the Cox model. Under proportional hazards, these residuals should be independent of time. A formal hypothesis test (often called the Grambsch-Therneau test) evaluates whether the correlation between scaled Schoenfeld residuals and time (or a transformation of time, such as log-time) is significantly different from zero. A p-value below 0.05 indicates a statistically significant violation of the PH assumption.
Actionable Steps: Resolving Non-Proportional Hazards
When the proportional hazards assumption is rejected, researchers must transition to an alternative modeling framework. Simply ignoring the violation is not an option. Here is the established clinical pathway for addressing non-proportional hazards:
| Step | Statistical Action | Clinical & Quality Gate |
|---|---|---|
| 1. Diagnosis | Run the Grambsch-Therneau test on scaled Schoenfeld residuals and plot residuals against time. | P < 0.05 on the global or individual covariate tests establishes non-proportionality. |
| 2. Stratification | If a baseline categorical confounder (e.g., center or disease stage) violates the PH assumption, use a stratified Cox model. | Allows baseline hazards to differ across strata while maintaining common treatment effects. |
| 3. Time-Varying Coefficients | For primary treatment effects that vary, fit an extended Cox model with an interaction term between the treatment and a function of time (e.g., Treatment * ln(t)). |
Directly quantifies how the hazard ratio shifts over time, providing separate "early" and "late" HRs. |
| 4. Piecewise Constant HR | Partition follow-up time into clinically meaningful intervals (e.g., 0-6 months, >6 months) and estimate distinct hazard ratios for each interval. | Easy to interpret and present to clinicians; requires predefined, biologically plausible time splits. |
| 5. Restricted Mean Survival Time (RMST) | Calculate the area under the survival curve up to a prespecified clinically relevant time horizon (tau). | Provides an intuitive, assumption-free estimate of "life-years gained" that remains valid even when curves cross. |
Extended Cox Models with Time-Varying Coefficients
When the treatment effect changes over time, we can model the coefficient as a function of time. This is achieved by adding an interaction term between the treatment indicator and a function of time, such as log-time or linear time:
h(t | Z) = h0(t) * exp( beta1 * Treatment + beta2 * Treatment * g(t) )
Where g(t) is a specified function of time, commonly ln(t). Under this extended model, the hazard ratio is no longer a single number, but a function of time:
HR(t) = exp( beta1 + beta2 * g(t) )
This allows the hazard ratio to change continuously. For example, if beta2 is negative, the treatment becomes increasingly effective as time progresses (ideal for delayed effects). Reporting both beta1 and beta2 allows readers to calculate the treatment effect at any specific month of follow-up.
The Stratified Cox Model
If the violation of proportional hazards is caused by a baseline covariate (e.g., disease stage or trial site) rather than the primary treatment, a stratified Cox model is the simplest and most elegant solution. In a stratified model, the study population is divided into strata based on the violating covariate. Each stratum is allowed to have its own unique baseline hazard function h0_g(t), while the treatment effect beta is assumed to be identical across all strata:
h_g(t | Z) = h0_g(t) * exp( beta * Treatment )
This approach completely eliminates confounding from the stratifying variable and resolves the proportional hazard violation without adding unnecessary parameters to the model. However, a major limitation is that the effect of the stratifying variable itself cannot be estimated.
Evidence Summary Table
| Evidence or Methods Source | What it Supports | Evidence Level & Clinical Context |
|---|---|---|
| Grambsch & Therneau (1994) Biometrika |
Establishes the mathematical framework for testing proportional hazards using weighted Schoenfeld residuals. | Foundational methodology. Standard testing protocol implemented across all major statistical software packages. |
| Therneau & Grambsch (2000) Springer Statistics |
Provides detailed implementation guides for extended Cox models with time-dependent coefficients and stratified regression. | Gold-standard methodological textbook. Essential reference for clinical biostatisticians. |
| Bellera et al. (2010) BMC Med Res Methodol |
Reviews reporting of the proportional hazards assumption in oncology trials, highlighting common failures and reporting guidelines. | Methodological review. Urges mandatory reporting and validation of the PH assumption in all published oncology manuscripts. |
| Uno et al. (2014) Journal of Clinical Oncology |
Recommends Restricted Mean Survival Time (RMST) as a robust, assumption-free alternative to the hazard ratio under non-proportional hazards. | High-impact consensus guideline. Outlines clinical utility and interpretation of RMST in oncology trials. |
Methodological Pitfalls to Avoid
When dealing with non-proportional hazards, investigators frequently fall into several statistical traps. Avoid these common reporting and analysis failures:
- "The Average HR Fallacy": Reporting a single hazard ratio from a violated Cox model. This hazard ratio is a weighted average of the true hazard ratios over time, heavily biased by early events. It does not represent the treatment's true efficacy at any single point in time.
- Inappropriate Testing Selection: Relying solely on graphical inspection (Kaplan-Meier curves) without conducting a formal Schoenfeld residual test, or assuming that a non-significant Schoenfeld test in a very small sample means the assumption is met (low power).
- Misinterpreting Time-Varying Covariates: Confusing time-varying coefficients (the treatment effect changes over time) with time-varying covariates (the values of the baseline variables themselves change over time, such as repeating lab values). They require completely different coding and modeling structures.
- Arbitrary Time Splits: Creating piecewise constant models with arbitrary time cuts (e.g., partitioning at 3 months because it "looks nice" on the curve). Time splits must be biologically or clinically justified, or pre-specified in the protocol.
Researcher's Toolkit: Address Non-Proportional Hazards
Leverage the specialized tools at Lingcore SCI to optimize and audit your survival analyses:
- Paper Analyzer: Input your manuscript or protocol to automatically audit survival analysis reporting, extract Schoenfeld residual testing details, and verify if violation remedies conform to STROBE/CONSORT guidelines.
- Review Builder: Build a citation-linked literature synthesis comparing the clinical utility of hazard ratios, RMST, and extended Cox models under delayed treatment effects.
- Journal Matcher: Identify high-impact journals in oncology, cardiology, and clinical methodology that prioritize advanced biostatistical reporting and robust causal survival analyses.
These tools are designed to facilitate evidence synthesis and reporting alignment. Researchers are solely responsible for verifying statistical assumptions, model specifications, clinical interpretations, and regulatory compliance before submitting manuscripts or making clinical trial decisions.
Conclusion
The proportional hazards assumption is not a mere statistical formality; it is a clinical and biological assertion about how a treatment works. Non-proportional hazards represent valuable clinical information, indicating that a therapy's effect is delayed, waning, or highly dependent on patient heterogeneity. Rather than ignoring a violated assumption or treating it as a failure, researchers should embrace the opportunity to tell the complete clinical story.
By executing scaled Schoenfeld residual tests, applying stratified Cox models for confounders, specifying extended Cox models for treatment interaction with time, or reporting Restricted Mean Survival Time, investigators can produce robust, review-proof manuscripts that reflect the true temporal dynamics of therapeutic interventions. Matching the statistical remedy to the clinical mechanism of non-proportionality is the key to turning a methodological challenge into a scientific breakthrough.
Medical Disclaimer
This article is for medical research and educational purposes only. It does not provide medical advice, diagnosis, treatment recommendations, or a substitute for clinical, statistical, regulatory, or institutional review. Researchers must verify the cited sources, baseline hazard assumptions, residual diagnostics, and alternative model specifications before utilizing survival analysis in any clinical study or decision-making process.