 LINGCORE SCI
Bayesian Model Averaging in Clinical Research: Managing Model Uncertainty Beyond Stepwise Selection
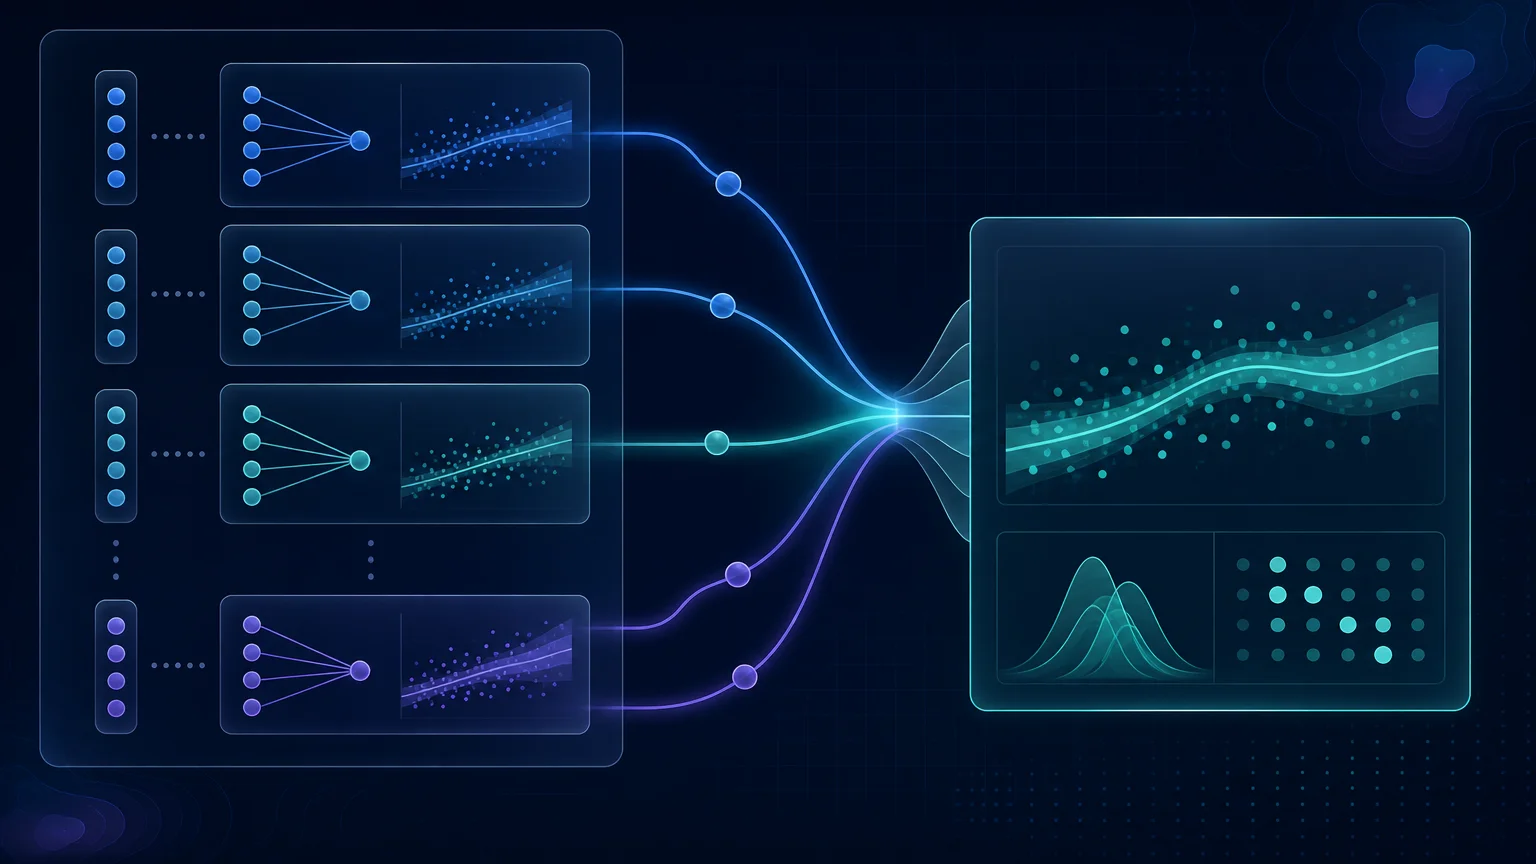
Bayesian model averaging (BMA) manages model-selection uncertainty by combining inference across plausible models instead of treating one selected model as known. It can reduce overconfident variable-selection claims, but it does not eliminate confounding, guarantee the correct model space, or replace calibration, balance diagnostics, sensitivity analysis, and external validation.
Medical researchers frequently face a deceptively simple modeling question: which covariates belong in the final regression model? The candidate list may include demographic variables, comorbidities, laboratory measurements, prior treatments, biomarkers, and care-setting characteristics. A conventional workflow often selects one subset using forward, backward, or stepwise procedures and then reports the resulting coefficients as if the selection process had never happened.
That workflow hides a second layer of uncertainty. The analyst is uncertain not only about the coefficients within a model, but also about which model generated the data well enough to support the planned interpretation. Two reasonable variable-selection strategies can produce different covariate sets, effect estimates, standard errors, and clinical narratives. Bayesian model averaging addresses this problem by retaining a collection of plausible models and combining their posterior contributions.
BMA is therefore better understood as an uncertainty-management framework than as a faster variable-selection algorithm. It can support risk-factor modeling, clinical prediction, and propensity-score analysis, but its conclusions remain conditional on the candidate model space, prior distributions, likelihood, computation, and data quality. Averaging many models does not make a poorly defined clinical question causal, and it does not make an unvalidated prediction model ready for implementation.
Why a single selected model can be misleading
Stepwise selection is attractive because it produces a concise model and familiar output. The difficulty is that repeated candidate testing and selection are part of the analysis, even when the final table shows only the selected variables. If several covariate combinations fit the data similarly, the reported coefficient may reflect a selection path rather than stable evidence about the underlying association.
Model uncertainty is especially important when predictors are correlated, the number of candidate variables is large relative to the sample size, the outcome is rare, or subject-matter knowledge is incomplete. A variable may be included in one plausible model and omitted from another without a meaningful change in predictive performance. Treating inclusion as a binary fact can make the evidence appear more certain than it is.
Bayesian model averaging changes the target of the analysis. Rather than asking only which model wins, it asks how much posterior support is distributed across the model space and how the parameter or prediction changes after averaging over that support. The result can be a posterior inclusion probability, a model-averaged coefficient, a model-averaged risk prediction, or a treatment-effect estimate that includes uncertainty about the selected covariates.

What Bayesian model averaging actually averages
Suppose a research team defines a set of candidate models, each containing a different combination of predictors. BMA assigns a prior probability to each model and updates that probability using the data. Models with greater posterior support contribute more to the final averaged inference, while models with little support contribute less. The averaged result is not necessarily the coefficient from the single model with the highest posterior probability.
For a predictor, the posterior inclusion probability summarizes the posterior support for models that include that predictor. A model-averaged coefficient can incorporate both the estimated coefficient within models where the variable is present and the probability that the variable is included. The exact interpretation depends on how the averaging is defined and which model family is used.
Posterior inclusion probability is not the probability that a clinical factor is biologically important, harmful, or useful for decision-making. It is conditional on the model space, prior, likelihood, data, and coding choices. A low inclusion probability may reflect weak evidence, collinearity with another predictor, limited sample size, an incomplete candidate model space, or a prior that favors simpler models. A high inclusion probability does not prove causality, clinical importance, or transportability.
The correct interpretation is therefore conditional and comparative: under the specified candidate models and prior assumptions, how strongly does the data support including this variable, and how stable is the associated effect across plausible models? That is more informative than presenting a selected-variable list without showing how sensitive it is to alternative specifications.
Model space, priors, and computation
A defensible BMA analysis begins before the sampler or model-fitting routine runs. The analyst must define the candidate model space, including which variables may enter, whether interactions or nonlinear terms are allowed, whether clinically essential covariates are forced into every model, and whether certain combinations are prohibited because they create redundancy or violate the causal design.
The prior over models can favor smaller or larger models, while parameter priors influence the marginal likelihood and posterior estimates. Zellner-type g-priors and Bernoulli inclusion priors are common examples, but no default is automatically correct for every medical study. If prior information is weak, the analyst should state that explicitly and perform sensitivity analyses under reasonable alternatives. If the study has strong external evidence, an informative prior may be defensible only when its origin, scale, and compatibility with the current population are described.
Computational strategy matters because the number of possible models grows exponentially with the number of candidate variables. Exact enumeration may become infeasible. Approximate methods, stochastic search, Markov chain Monte Carlo, Occam’s window, or other model-space reduction strategies may be used. The manuscript should report the search method, number of iterations, burn-in, thinning when relevant, convergence diagnostics, effective sample size, model-space restrictions, and how posterior summaries were calculated.
BMA versus stepwise selection
Medical simulation studies have compared BMA with stepwise approaches under specified data-generating conditions. In one simulation study, BMA had a higher probability of avoiding redundant variables than stepwise regression while maintaining a similar or higher probability of selecting true predictors. A matched case-control application likewise reported lower false-positive selection and more robust effect estimates with BMA than with a classical selection approach.
These findings do not support a universal statement that BMA always outperforms stepwise selection. Simulation performance depends on the correlation structure, effect sizes, outcome prevalence, sample size, prior, model space, and evaluation criterion. A method that performs well in one data-generating process may behave differently when predictors are strongly collinear, missingness is informative, the event is rare, or the true relationship is nonlinear.
The more useful comparison is conceptual. Stepwise selection returns one path-dependent subset and usually treats the final model as fixed. BMA retains model uncertainty and summarizes how inference changes across plausible subsets. If the scientific goal is explanation, the model space should be guided by subject-matter knowledge and causal structure. If the goal is prediction, BMA should be compared with penalized regression, ensemble methods, and other candidates using resampling, calibration, discrimination, and external validation.
Use in clinical risk prediction
BMA can be used during risk-model development when investigators want to represent uncertainty about which predictors and functional forms belong in the model. A model-averaged prediction can account for multiple plausible specifications rather than relying on one selected equation. This can be helpful when the candidate set is broad but the study team wants to avoid presenting one arbitrary model as definitive.
Variable inclusion uncertainty does not replace prediction-model evaluation. The final analysis should report discrimination, calibration, clinically relevant thresholds, decision-curve or utility measures when appropriate, optimism correction, and external validation. A model with stable inclusion probabilities can still be poorly calibrated in a new setting. Conversely, several models may produce similar predictions even when their individual coefficients differ, which can be important when deciding whether a stable risk estimate is possible without stable variable selection.
Risk-prediction research should distinguish between a model used to estimate association and a model used to make predictions. The predictors needed for accurate prediction may not be causal risk factors, and a high posterior inclusion probability does not establish that intervening on the variable will change outcome risk. The target population, prediction horizon, outcome definition, and intended decision must remain explicit.
Use in propensity-score and causal analysis
BMA can also address uncertainty in the variable-selection equation for a propensity score. In this setting, analysts may average across plausible treatment-assignment models and propagate that uncertainty into the estimated treatment effect. A published propensity-score application found that Bayesian model-averaging approaches generally recovered treatment effects well, produced larger uncertainty estimates as expected, and showed good covariate balance in the reported case study.
These findings do not mean that BMA resolves confounding. The treatment assignment model still requires a clinically defensible covariate set, and the causal interpretation still depends on consistency, conditional exchangeability, positivity, treatment timing, missing-data handling, and outcome analysis. Covariate balance should be checked after weighting, matching, or stratification. Extreme propensity scores, effective sample size, weight variability, overlap, and sensitivity to omitted confounding remain relevant.
Analysts should also prevent inappropriate information flow. If post-treatment outcome data feed back into the propensity-score equation, the treatment-selection model can be distorted. A sequential or two-step design may be preferable to an indiscriminate joint model, depending on the estimand and software. The analysis plan should specify whether model uncertainty is propagated only in the propensity score, in the outcome model, or jointly, and how the posterior treatment-effect distribution is summarized.
Actionable Steps: Build a defensible BMA analysis
| Step | Research action | Quality gate |
|---|---|---|
| 1. Define the target | State whether BMA supports etiologic association, prediction, treatment-effect estimation, propensity-score adjustment, or another estimand. | The outcome, exposure or treatment, time horizon, and target population are specified before model selection. |
| 2. Build the model space | List candidate predictors, interactions, nonlinear terms, forced covariates, exclusions, and clinically required adjustment variables. | The model space is clinically justified and does not silently omit important confounders or create impossible combinations. |
| 3. Predefine priors and computation | Document model and parameter priors, search or MCMC strategy, burn-in, iterations, convergence diagnostics, and model-space reduction. | Another analyst could reproduce the posterior model search and evaluate convergence. |
| 4. Report averaged inference | Present posterior model probabilities, inclusion probabilities, model-averaged effects or predictions, uncertainty intervals, and sensitivity to prior choices. | Readers can distinguish model uncertainty from ordinary coefficient uncertainty. |
| 5. Validate the use case | For prediction, assess calibration, discrimination, utility, and external validation; for causal analysis, assess balance, positivity, assumptions, and sensitivity. | BMA is evaluated for the intended clinical task rather than judged only by variable-selection output. |
Common analytical and reporting failures
The first failure is presenting BMA as a magic solution to variable selection. The method still depends on the candidate model space, priors, likelihood, computation, and observed data. If a clinically important confounder is absent from the candidate set, model averaging cannot recover it.
The second failure is interpreting posterior inclusion probability as a probability of clinical importance or causality. Inclusion probability expresses support for a variable under the selected model space and prior. It should be interpreted alongside effect size, uncertainty, clinical relevance, measurement quality, and the study design.
The third failure is reporting only the highest-probability model. That discards the central reason for using BMA. Report the model distribution, the averaged effect or prediction, the main contributing models, and the sensitivity of conclusions to prior and model-space choices.
The fourth failure is comparing BMA with a weak or under-specified stepwise model and claiming superiority. Use comparable candidate variables, outcomes, validation datasets, and performance measures. Simulation findings should be described with their data-generating conditions rather than generalized to every clinical dataset.
The fifth failure is skipping calibration or covariate-balance diagnostics. Prediction models need calibration and external validation. Propensity-score applications need overlap, balance, weight, and effective-sample-size checks. A lower false-positive selection rate does not establish clinical utility.
The sixth failure is using BMA to justify post hoc storytelling. If a variable has moderate inclusion probability and a wide model-averaged interval, the uncertainty is part of the result. It should not be compressed into a binary selected/not-selected claim simply to create a cleaner narrative.
Evidence Summary Table
| Evidence or methods source | What it supports | Level and boundary |
|---|---|---|
| Mu et al., 2019 PubMed record | BMA considers models with non-negligible posterior probabilities and reported lower false-positive selection and more robust effects in simulation and matched case-control application. | Simulation plus applied study; findings depend on the data-generating process and model specification. |
| Wang et al., 2010 PubMed record | Under specified simulations, BMA avoided redundant variables more often than stepwise regression while maintaining similar or better true-predictor selection. | Medical simulation; not a universal ranking of methods. |
| Mu et al., open-access full text PMC article | Explains posterior model probabilities, MCMC computation, model-space growth, and model-averaged inference. | Methods and applied case-control paper; computation and priors require reporting. |
| Crespi et al. PMC article | Demonstrates BMA in selection of a clinical risk-prediction model. | Application; prediction performance and external validation remain necessary. |
| Antonelli et al. PMC article | Uses BMA to address propensity-score model uncertainty and reports treatment-effect, uncertainty, and balance implications. | Causal-methods application; BMA does not remove confounding or positivity requirements. |
| Hoeting et al., 1999 Tutorial DOI | Provides the foundational framework for Bayesian model averaging in prediction and inference. | Foundational tutorial; implementation must be adapted to the clinical estimand. |
Researcher's Toolkit: Audit Model Uncertainty
Use Lingcore SCI tools to organize and quality-check Bayesian model-averaging research:
- Paper Analyzer: Extract model space, priors, posterior inclusion probabilities, computational strategy, convergence diagnostics, and validation results.
- Review Builder: Build a citation-linked comparison of BMA, stepwise selection, penalized regression, and ensemble prediction approaches.
- Journal Matcher: Compare journals publishing Bayesian biostatistics, clinical prediction, causal inference, epidemiology, and medical methodology.
These tools support evidence organization and reporting quality. Researchers remain responsible for the estimand, model space, priors, diagnostics, validation, and clinical interpretation.
Conclusion
Bayesian model averaging makes model-selection uncertainty visible by combining inference across plausible models rather than treating one selected equation as known. In medical simulations and applications, it has shown potential to reduce redundant variable selection and provide more robust or appropriately wider uncertainty estimates under specified conditions.
BMA is not a substitute for clinical reasoning, causal design, calibration, balance diagnostics, sensitivity analysis, or external validation. A rigorous analysis defines the model space, justifies priors, documents computation and convergence, reports averaged effects and inclusion probabilities, and evaluates the method against the intended clinical task. Used this way, BMA can replace false certainty with a more transparent account of what the data support and what remains uncertain.
Medical Disclaimer
This article is for medical research and educational purposes only. It does not provide medical advice, diagnosis, treatment recommendations, or a substitute for clinical, statistical, regulatory, or institutional review. Researchers must verify the cited sources, assumptions, data quality, model specification, and validation results before using Bayesian model averaging in a study or decision.